
ADA tier
- What we cast
- Gold-based casting alloys; platinum-containing alloys
- Typical application
- First-choice retainer for bruxers, long-span bridges, patients with Ni/base-metal history
- Color
- Yellow or white (platinum-containing alloys are white)

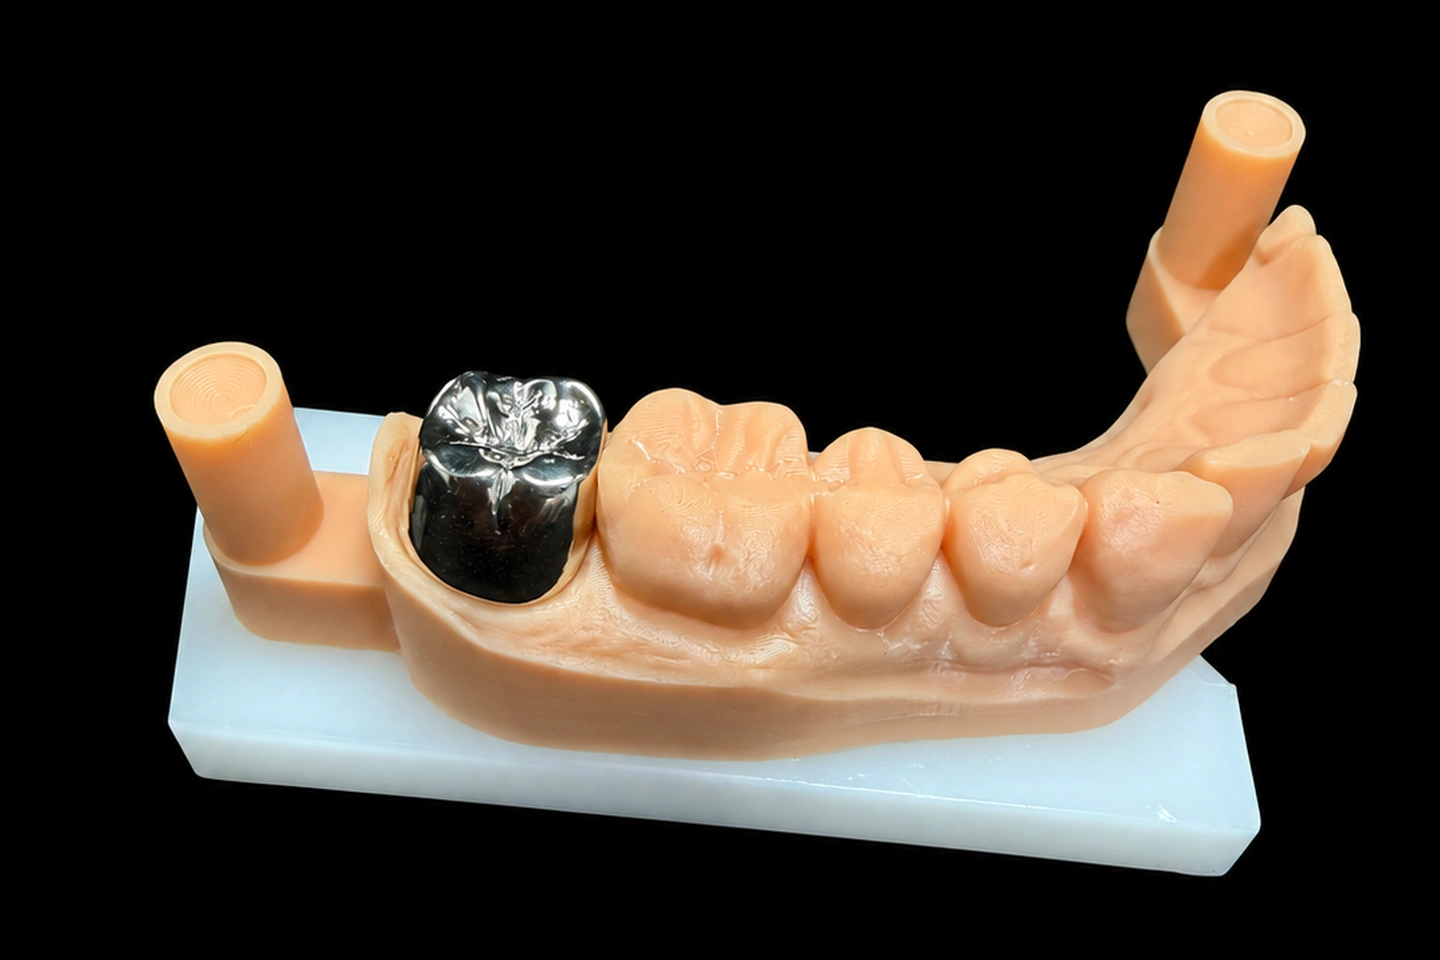
Full Cast Metal Crowns are single-piece metal restorations with no ceramic veneer. Because there is no porcelain layer, the restoration can be made thinner than a PFM, which matters when you have a short clinical crown, limited occlusal clearance, or a bruxer who keeps breaking ceramics. At Istar Dental Lab we cast and mill them in-house, from CAD design through final polish and QC. This page is written for the dentist, the clinic owner, the DSO procurement lead, and the outsourcing lab who needs to know exactly what we can do, under what prep window, in what alloy, in how many business days, and under what remake policy.
A full-metal design is the quietest choice when esthetics is not the primary constraint. The real decision happens on four axes:
What it is not the right call for:
The numbers below are the clinical-teaching values we use when checking an incoming case, cross-referenced to standard operative dentistry teaching. If your prep is tighter than this on one axis, tell us at Rx submission so we can confirm whether we can still deliver an acceptable restoration or whether a re-prep is faster than a remake.
| Dimension | Target | Why we flag it |
|---|---|---|
| Functional cusp reduction | 1.5 mm | Below this the metal thickness drops into deformation territory under heavy load |
| Non-functional cusp reduction | 1.0 mm | Needed for occlusal thickness without a hollow |
| Axial reduction | 1.0 mm at marginal ridge, 0.6 mm at cervical | Too little and we cannot cast a cleansable contour |
| Margin design | Chamfer or light shoulder, 0.5 mm metal collar | Knife-edge margins are the single most common cause of fit disputes we see from scanned prep data |
| Total occlusal convergence | ~6° per wall | Over-tapered walls lose retention; parallel walls will not seat |
| Functional cusp bevel | ~45° | Protects the metal from thin, chipping edges along the occlusal line angle |
| Margin location | Supragingival where esthetics allows | Reliable scan/impression capture; easier post-cementation hygiene |
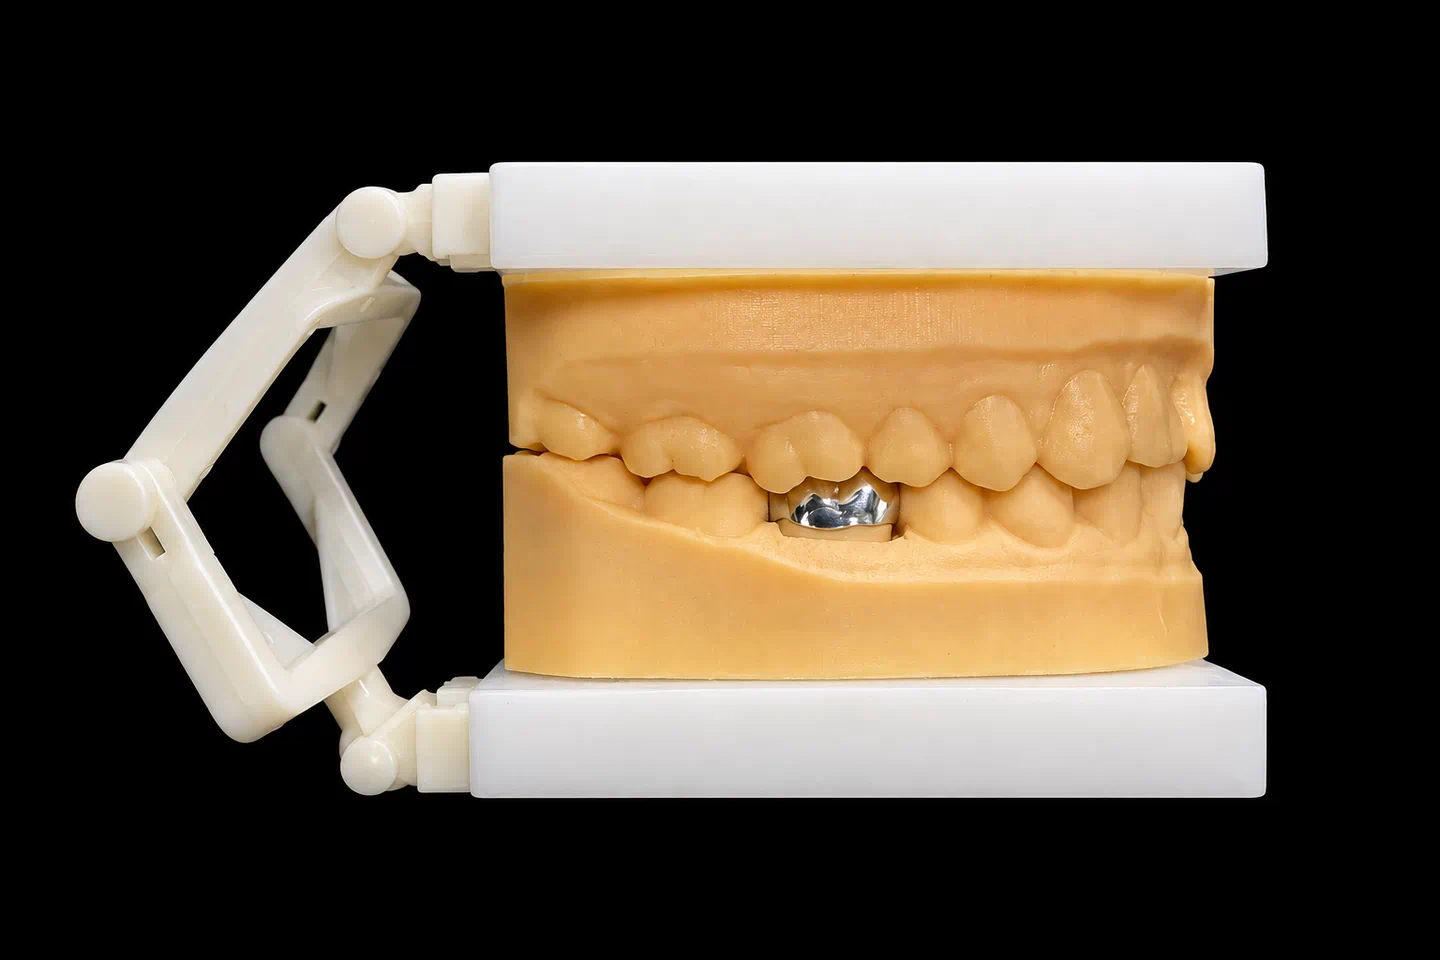
In a 2024 systematic review and network meta-analysis of 261 crowns across 177 subjects with up to 24 months of follow-up, mean antagonist enamel loss versus natural-tooth controls was +82.5 µm opposing metal-ceramic, +40.1 µm opposing monolithic zirconia, and +5.0 µm opposing lithium disilicate (Mao et al., Journal of Dentistry). The review did not break out full cast metal as a separate arm, so we cannot quote a direct number for it. The biological rationale that polished high-noble gold is kind to opposing enamel is well established, but a quantified head-to-head value for cast gold against modern ceramics is not available in the current peer-reviewed literature we have found. If a specific µm value matters for your case documentation, ask us and we will share what we have.
We offer four alloy groups across the three ADA tiers, as defined by the ADA's materials classification (Materials for Indirect Restorations). The choice is driven by biocompatibility history, mechanical demand, and budget — color follows composition, not the other way around.
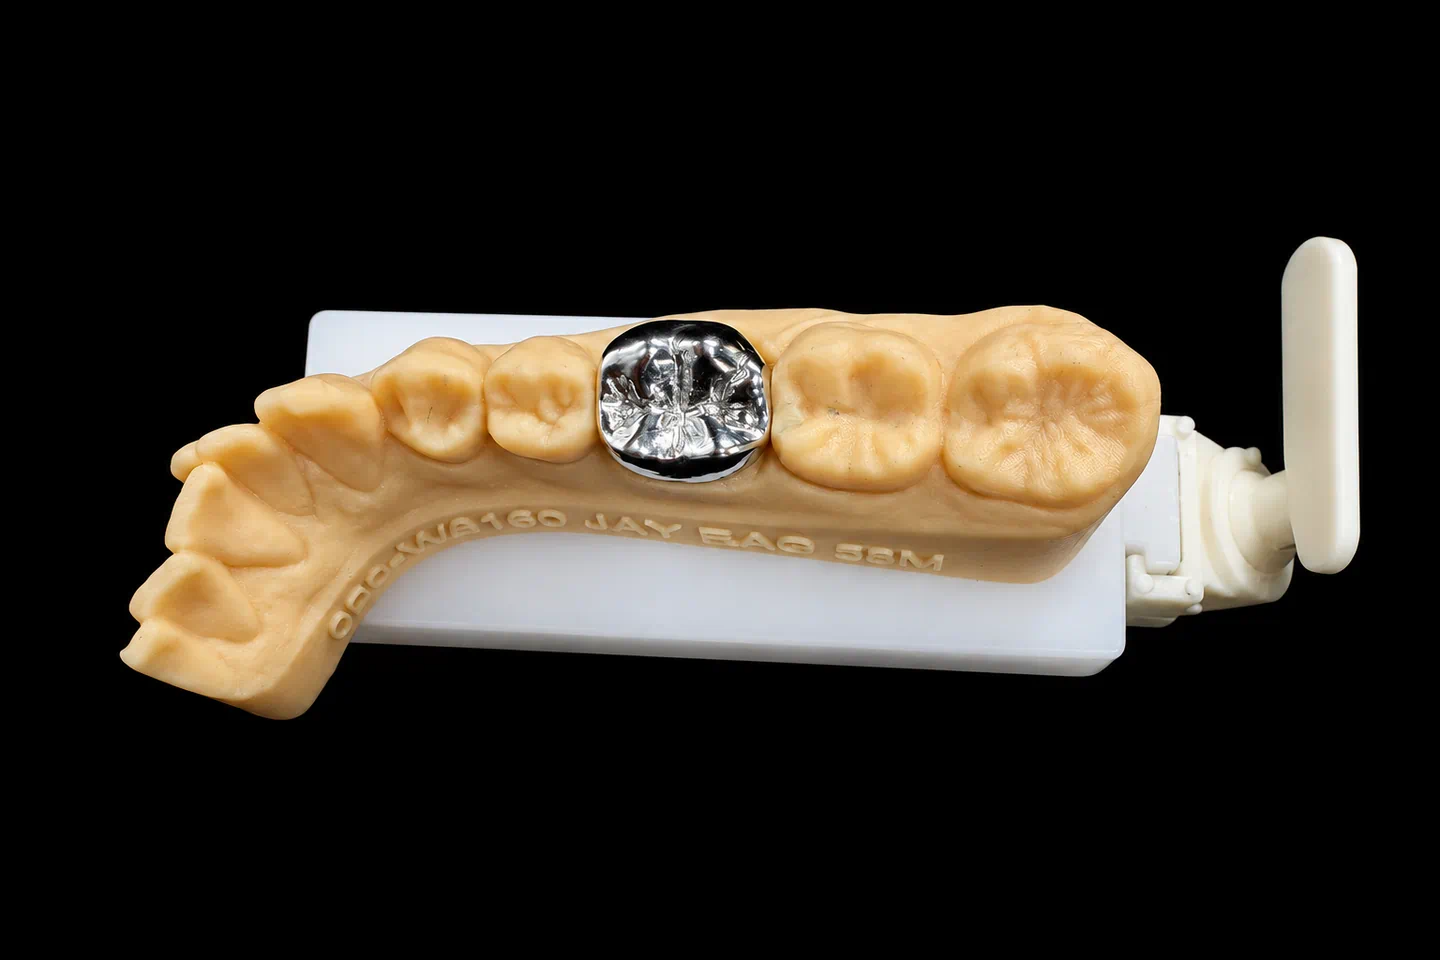
Two facts worth stating up front because they are a common source of case-coordination disputes:
For every case we can provide the alloy brand, country of origin, lot number, and the manufacturer's composition certificate. Nickel-containing base-metal alloys and beryllium-containing alloys are regulated as Class II dental devices under 21 CFR 872.3710, and we comply with the composition-disclosure part of that framework. We do not use "hypoallergenic" as a product claim because the published prevalence range for intraoral metal allergy spans 3%–91% depending on study population and method (Khamis et al., PubMed 42106203), and a single-point number would misrepresent that evidence. If you have a patient with a confirmed patch-test result for a specific metal, send us the allergen list and we will select an alloy and provide the matching composition certificate.
Istar Dental Lab was founded in 2012. We operate from facilities in Shenzhen and Huizhou, with roughly 460 full-time staff including a 100-person CAD design department, a 70-person milling team, a 70-person ceramics and metalwork team, and a 25-person quality control team. We do not outsource case production to third-party labs; everything from CAD through final QC runs inside our own plants.
For a Full Cast Metal Crown the in-house workflow is:

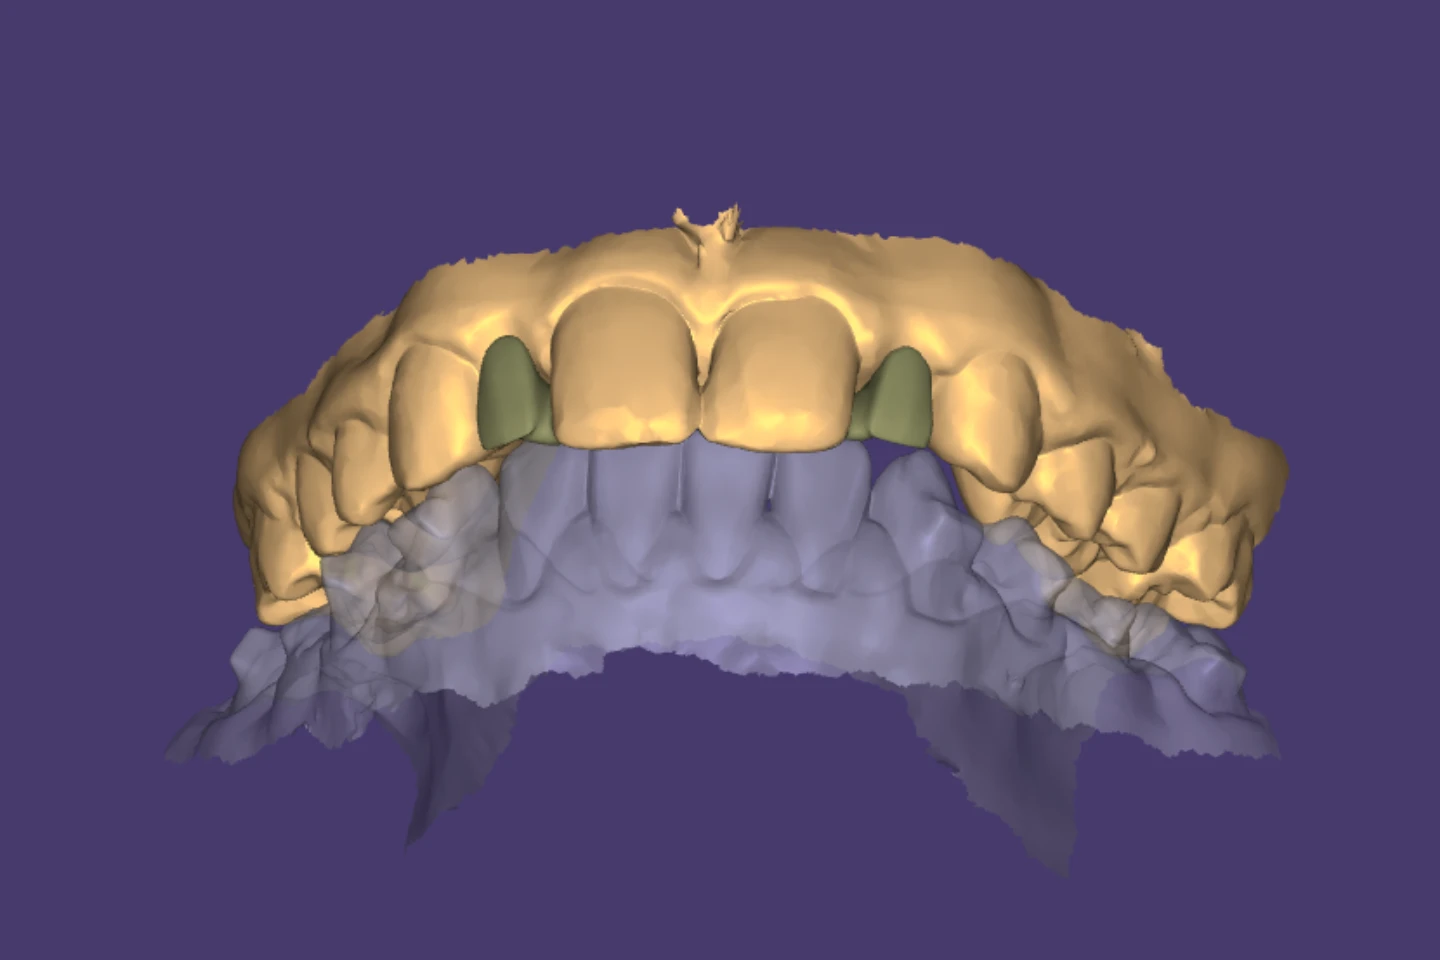





Final QC covers margin seal and continuity, internal surface (no spurs, voids, or pressure spots), interproximal contact tightness on the master model, static and excursive occlusion, and the metal thickness at functional and non-functional cusps measured with a thickness gauge or micrometer. For every case we can send photographs of the finished crown on the model before shipping — ask once at account setup and it becomes the default for your account.
Internal rework rate across all restoration categories currently runs at 2–3% of production. Trends are reviewed monthly, broken down by product line and root cause, and corrective actions are logged. If you want a monthly on-time, remake, and complaint report for your account, we can produce that for group and DSO clients.

Our quality system is covered by ISO 13485. We hold FDA establishment registration and device listing for US-market dental restorations, UK MHRA registration via a UK Responsible Person, and EU MDR custom-device notification (Annex XIII pathway) through an authorized representative. Materials are supplied with CE marking and biocompatibility documentation per the ISO 10993 series.
Case-level traceability is standard. Each case is bound to a unique order number that links the responsible designer, production technician, equipment used, material batch, and QC results. Case records are kept for three months by default; if your compliance program requires longer retention, say so at account setup and we will extend it for your account.
Factory audits are supported. We welcome scheduled on-site visits in Shenzhen and Huizhou, video audits via live stream, and documentation review for quality-system records, material certificates, and process logs.
We do not publish a flat per-unit retail number for Full Cast Metal Crowns because the final line depends on the alloy class and the design complexity, and quoting an average would be misleading. The structure is:
Rush production is available on all case types. For dentist-direct accounts, up to 10 rush cases per calendar month carry no rush surcharge; above that volume, rush is quoted per case. Rush availability is confirmed at Rx stage, not after. Payment accepts bank wire and PayPal; account terms up to 30 days are available after new-account review.
We dispatch via DHL, FedEx, UPS, and (for France) SPIDER. Return shipping is covered by Istar above an account-specific case-value threshold. Clearance, duties, broker fees, and remote-area surcharges are on the receiver. Default shipments go without declared insurance; declared value with carrier insurance is available on request and is quoted per shipment.
The clock starts the working day we confirm the case is complete. Design-approval wait, missing Rx fields, and additional information requests do not count against the posted turnaround; the clock resumes when you confirm. Weekends and Chinese public holidays are not counted. International carrier time is additional and is quoted separately.
For digital cases the overall calendar time is shorter because there is no physical-impression transit on the inbound leg. Status notifications are sent at design-complete, production-complete, and dispatch; the dispatch message carries the tracking number.
Report any issue within 24 hours of receipt. The report should include case ID, patient reference, product type, the specific issue, and intraoral or model photos documenting it.
We remake at no additional lab fee for: open margin, open contact, high occlusion, failure to seat, color drift from the Rx, visible cosmetic defect, and poor contour. For a remake, the physical restoration must be returned; digital-only cases can be reproduced from the stored file. Lab-fee-free remake does not cover return shipping or implant components, which are quoted separately.
We do not cover under free remake: customer-initiated changes to color, alloy, or design after the case was approved; cases where the Rx requested production despite a documented poor impression; and cases where a different clinical outcome is being pursued after the restoration was already seated.
Remake priority is 3–5 working days in our schedule. If a remake fails on a second attempt we escalate the case to the production manager and the technical director; if a working outcome still cannot be delivered we offer a credit or a refund rather than a third remake.
MRI. A cast metal crown does not contraindicate MRI. The material produces local susceptibility artifact that is generally smaller than ferromagnetic materials, but the imaging team should be told the restoration is present and the alloy composition should be available on request (Hilgenfeld et al., PMC10043623).
Cementation. In a 3,468-crown US practice-based study, 61.9% of single-unit crowns were seated with a non-resin cement (primarily resin-modified glass ionomer) and 38.1% with a resin cement (Makhija et al., PMC6538426). For retentive preps on a cast metal retainer, RMGI is a defensible first choice; short preps or retainer-on-tapered-abutment designs are often better served by a resin cement with a metal primer. Choose per case; we are happy to discuss on complex retainers.
Food packing. Food traps on a seated crown are almost always a contact or marginal-ridge-contour issue, not a material issue. If a patient reports packing after cementation, send us a photo or scan of the seated restoration in situ and we will quote on a reshape or remake depending on the finding.
Send us the following and we will respond with buildability and a case-specific quote on the next working day:
Contact Istar Dental Lab — our sales team confirms account setup, pricing, and buildability. Factory visits (Shenzhen or Huizhou) and video audits can be scheduled with the same contact.
Want to get in touch directly? Reach out to our sales representative via WhatsApp at +8618925410015 for a quick response and a price quote!
 Dental Guide
17 min read
When cementing a porcelain-fused-to-metal (PFM) crown, most guides hand you a list of cement types and leave you to guess. But U.S. practice data shows only 13.8% of PFM crowns are resin-bonded—the…
Read Article Dental Guide
11 min read
The practical questions around glazing zirconia crowns rarely come down to a single yes-or-no answer. A review of monolithic zirconia finishing notes that a standardized finishing protocol for this material has yet…
Read Article Dental Guide
10 min read
A multilayer zirconia crown is milled from one zirconia disc whose shade and translucency change along its vertical axis — more chroma near the cervical zone, more translucency toward the incisal edge.…
Read Article